

Toni
Contributor
- Joined
- Aug 10, 2011
- Messages
- 25,018
- Basic Beliefs
- Peace on Earth, goodwill towards all
Scores are what gets everyone in.Fairly sure my score got me in, during undergrad I was very, um..., er,... social.
Scores are what gets everyone in.Fairly sure my score got me in, during undergrad I was very, um..., er,... social.

You and your ilk cannot explain any reduction in white men’s chances without screaming discrimination. The notion that the world does not revolve around white men is inconceivable to you.The evidence is in the data about MCAT and GPA distribution for matriculated students. You and your Ilk still have not found a way to explain it without admitting discrimination in the name of "diversity", aka "affirmative action".
Nobody disagrees that there was discrimination in the past. But that does not justify discrimination today. Whether it is to improve "diversity" or for some other supposedly noble purpose.Policies have always been set, both explicitly and implicitly, to favor a particular gender and race and perceived sexual orientation. Historically—in fact until not very long ago the preferred candidates were: Straight, white and male. Preferably Christian or Christian adjacent, preferably not Catholic and not Jewish. Within some communities, those who did not fit that niche, some were able to rise to positions of influence, power and wealth.
Straight white males should not be first in line, but we should not be last in line either, or rather second last (Asians are dead last).For a lot of perfectly nice people, the perception that the only reason straight white male is no longer the first in line is that others are being given preferential treatment—and ignoring the fact that their perception has been based upon the long established precedent of straight white male being the best choice.
Even if they have to discriminate against students belonging to "overrepresented" groups to accomplish that goal.I’ve talked with enough admissions counselors to know that admissions seeks to built a class that does not reflect the same very narrow world that most incoming first year students are accustomed to—but to bring together people of diverse backgrounds and experiences and talents.
So why have different admission standards by race? Because unless you claim that blacks outperform whites and Asians on some metrics that cancel the advantage whites and Asians have on academic performance, then the only other possibility that explains the data is that med schools are discriminating by race and ethnicity.Because the world is a big wonderful place full of of many different kinds of people and that their talents, skills, ambitions, and abilities are not allocated by race, gender, sexual orientation ration/expression , class, ethnicity, first language or country where they or their parents or grandparents were born.
That was a disgrace to the franchise. And it is quite hypocritical for a feminist like you to enjoy objectification of men after making your entire brand about opposition to objectification of women.That said, Ghost Busters with Hemsworth as the sexy secretary was a hoot and a half.
 And note that this is not what happened in the original Ghostbusters. They did not cast Kelly LeBrock or somebody and put her in skimpy clothing.
And that's where academic qualifications come in. In order to advance in their med school journey, med students must pass USMLE Step 1. And passing it on first try is heavily linked to both MCAT and GPA.But still: Universities and Med schools, law schools, vet schools, grad and professional schools gave a lot riding on admitting students who will be successful.
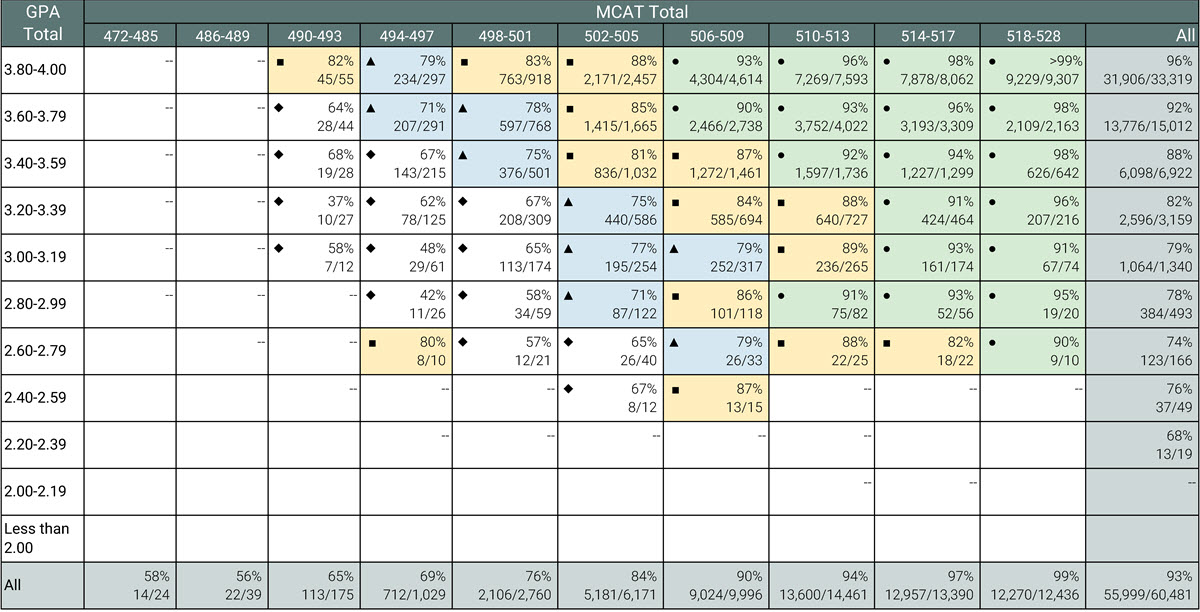
Nobody is says it is. But it is very indicative of one's academic performance.Not every important or necessary quality is reflected in GPA or MCAT scores.
I don't know my doc's MCAT scores of course, but I do know where he went to med school, and I also know that he got his undergrad degree from my alma mater.Which do not matter at all after you are admitted. Seriously: Do you know your doctor’s MCAT scores? Or even where they attended medical school? Does that matter?
It's really two significant figures for MCAT. The score is between 472 and 528, for 56 total points, or 14 per section.You are all digging around in the noise, looking for a signal that can't possibly be there.
Test scores presented to three significant digits are a great example of spurious accuracy.
No, a pass-fail system is not sensible at all. It does not distinguish between somebody barely passing and somebody doing really well.A sensible system would just give everyone with an MCAT above 505 a "pass" grade, and not bother to reveal the exact score, on the basis that exact scoring is not an exact representation of anything useful.
While standardized tests are certainly far from perfect, they are certainly orders of magnitude less crude than subjective metrics like essays or the interview or letters of recommendation that apparently certain people think med schools should rely on more.Examiners and examination boards won't ever admit it, but their ability to spot the best candidates for admission to a course (or to whom to award a degree or certification) is extremely crude. They hide this behind the spurious accuracy found in the raw test scores, from tests that are necessarily dramatically unlike real-world medical decision making.
Why? Those with higher scores performed better. Why is dumb luck a better system than performance? Even if that performance is not perfectly measured (and what is?) it does not follow that random chance is just as good, or even better. A yardstick with no graduations is a crude measuring device, sure, but it is certainly much, much better than just guessing the length of something based on vibes. Ah, it surely is more than 50 yards, no need to lay the stick end to end and actually measure it.An actual lottery would be no less inequitable than picking those with the highest MCAT score over those with lower (but still qualifying) scores.
Some people may freeze in a high pressure testing environment, but than again, they'll have to take similar tests in med school. However, I think the case you are making is overstated for sure.Some people do better on standardized tests regardless of their intelligence and educational background
Again, it's not everything, but academic preparation, and ability to reason from prior knowledge and information provided in the passage under time pressure is I think very much valuable for somebody in a medical profession, where they will have to apply their reasoning skills and prior knowledge to high stakes and often time-sensitive situations.and if anyone did a little research, they would realize as has been pointed out a few times, that MCAT scores do not make a good or a bad doctor.
They are also pretty much impossible to measure for premeds applying to med schools in any sort of objective way. And again, for the millionth time, NOBODY IS SUGGESTING THAT MCAT AND GPA ARE THE ONLY THINGS THAT MATTER!!!Things like emotional intelligence, willingness to keep learning, being open minded as new medical discoveries take place are far more important than MCAT scores.
Why single out white male doctors for derision?Plus, a a nurse who has dealt with both good and horrible doctors, imo, many doctors don't bother to learn much of anything new once they begin practicing. This, imo is very true of while male doctors, not all of them of course, but far too damn many of them. Gotta go. Have fun with this silly argument or find something better to do with your time.
Clinical evals are very much subjective, because a lot depends on the personality (and any biases) of the preceptor and the student's relationship with them. Also, clinical performance is not something that can be tested for purposes of med school admissions, but academic performance can be.I don't know about "objective," but if you look at the study that I had posted, you might say that the last two years of med school begin to predict how well one might do as a doctor. This is because hands-on training (and work) is being performed.
I think nixing Step 2 CS was a mistake for this reason. But again, this is not something relevant to admissions but to training further on. Unless you want to start requiring premeds to master skills like suturing before applying and have some way to reliably test tens of thousands of applicants on those skills.And there's also a kind of procedural dexterity: I remember in basic training, we were taught to shout some verbatim definition for an M16, but then later, shooting an M16 in target practice and scoring well is different from the capacity to shout a definition, and later on shooting an M16 on the battlefield is yet again different from target practice.
On a test like MCAT which has 56 points total, a difference of "twenty or thirty" is astronomical and yes, very much a matter of qualification.THANK you. I am constantly trying to make this point. If someone thinks that a difference of twenty or thirty "points" on a standardized exam is an important matker of essential, immutable "qualification",
It seems you yourself have not thought at all hard about what MCAT scores actually mean.either they haven't thought all that hard about what the points actually mean, or they'd do quite poorly themselves on any standardized measure of qualitative reasoning.
True that.I'm sure that once people are well into their training, predicting who will ultimately succeed becomes easier.
About twice as many, and that's applicants and not counting those who wanted to apply but thought better of it once they got their MCAT score back.The discussion thus far was around admittance. Realistically, there are probably more people who want to become a doctor than there are seats for med students.
I think combination of grades and MCAT is the best we've got. Can we improve the MCAT? Probably. But I think it the single best metric of academic preparedness we have.MCAT is a measure that can be used during admission. Are there other measures that might do a better job of it? Is there something that could replace MCAT, or is that essentially the best we've got?

NOR DOES THE SCORING SYSTEM.No, a pass-fail system is not sensible at all. It does not distinguish between somebody barely passing and somebody doing really well.
Indeed. You are just suggesting that they should be.NOBODY IS SUGGESTING THAT MCAT AND GPA ARE THE ONLY THINGS THAT MATTER!!!
I disagree.But it doesn't.
It is by far the most likely. The difference in the means is so high than it cannot be explained by chance. I have shown that statistically at the beginning of the thread.That may be a possible explanation for the observed differences, but it is not at all the only, or even the most likely explanation. You're working on incomplete data, and filling in the gaps with assumptions that you have no backing for. The assumptions you're making are driven by your belief.
I have shown that this is not so in post #91. The standard deviations are comparable, and means are far apart.The same outcomes could be explained by different standard deviations with in each cohort combined with different skew.
No credible alternative explanation has been offered, and it is known that academia champions the idea of "racial preferences". So why are people so reluctant to admit that this is also a case of racial preferences?You don't know what the driver of the differences are. You've latched on to your preferred narrative explanation - but you are no more justified in that assumption than are those who assume racism. Both are based on preconceived notions of what the cause is, without actual data to back it up.
I am not. I am just suggesting that there is no reason to assume other metrics are distributed in such a way that they largely cancel the different MCAT/GPA trends in absence of racial preferences on the part of adcoms.Indeed. You are just suggesting that they should be.
Is academic ‘preparedness’ the best indicator of who will make the best doctors?True that.I'm sure that once people are well into their training, predicting who will ultimately succeed becomes easier.
About twice as many, and that's applicants and not counting those who wanted to apply but thought better of it once they got their MCAT score back.The discussion thus far was around admittance. Realistically, there are probably more people who want to become a doctor than there are seats for med students.
I think combination of grades and MCAT is the best we've got. Can we improve the MCAT? Probably. But I think it the single best metric of academic preparedness we have.MCAT is a measure that can be used during admission. Are there other measures that might do a better job of it? Is there something that could replace MCAT, or is that essentially the best we've got?
That has less to do with standards required to enter med school than with the limited number of residency spots.In generalities, I agree. But I think there may be room for some squish that you're not taking into consideration. For example, it could be that in the past the bar has been set very high, as a means to limit the number of doctors, and thereby command higher rates.

There isn't some one-trick-pony "metric" that can magically tell you whether someone is a good candidate for medical school or not. Thank god you aren't sitting on any of these committees! Racism aside, you don't seem to understand how university application processes work in the slightest. It's not a question of "a-ha, this number is higher than x, they must be brilliant!"But let me ask you yet again: if not MCAT, which metrics do you think are more important for med school admissions? And how do you propose to assess premeds on these metrics?
Essentially you are arguing that MCT and GPAs are the only things that matter for admission to medical school and that any another “metric” (including one you don’t have access to ) leads to discrimination away from white men and/or Asians.I am not. I am just suggesting that there is no reason to assume other metrics are distributed in such a way that they largely cancel the different MCAT/GPA trends in absence of racial preferences on the part of adcoms.Indeed. You are just suggesting that they should be.

A bit old, but yes.This site is interesting:

Does MCAT Score Predict Success? Research Reveals Answer
Does MCAT score predict success? Explore research on exam predictability and discover how our MSMS program offers an alternative path to medical school success.msms.tiberhealth.com
Section you didn't quote:
So, MCAT scores predict success in med school. And while this website downplays the differences in retention rate, 2% vs 6% dropout means that low MCAT scorers have triple the risk of failing med school in the first year. That is a very significant difference. And due to lower MCAT scores of black, Hispanic and American Indian matriculants, far more of them fall into the dangerous 496-501 category.Tiber MSMS said:The MCAT Seems to Be Good at Predicting Academic Ability Early in Medical School
While the MCAT favors wealthier students, it does appear that students who achieve high scores on the MCAT, regardless of background, are likely to complete medical school. A 2013 study found that students with strong MCAT scores and GPAs at admission were more likely to experience “unimpeded progress” through medical school, meaning:
They were not dismissed for academic reasons
They did not withdraw for academic reasons
They graduated within five years of beginning medical school
They passed each step of the US Medical Licensing Exam (USMLE) on the first attempt
Further evidence supports this: the AAMC reports that 98 per cent of first-year medical students who scored in the average range (510-513) on the MCAT in 2019 progressed to their second year. However, so did 94 per cent of those with scores 10 points below the average (496-501).
That heading doesn't quite fit what's below.MCAT Success Doesn’t Seem to Translate to Clinical or Residency Success
So, an objective measure used for med school admissions is associated with objective measures in med school.- Associated with success on the USMLE step 1, the USMLE step 2 clinical knowledge exam, and the USMLE step 3
- Somewhat linked to higher GPAs during medical school
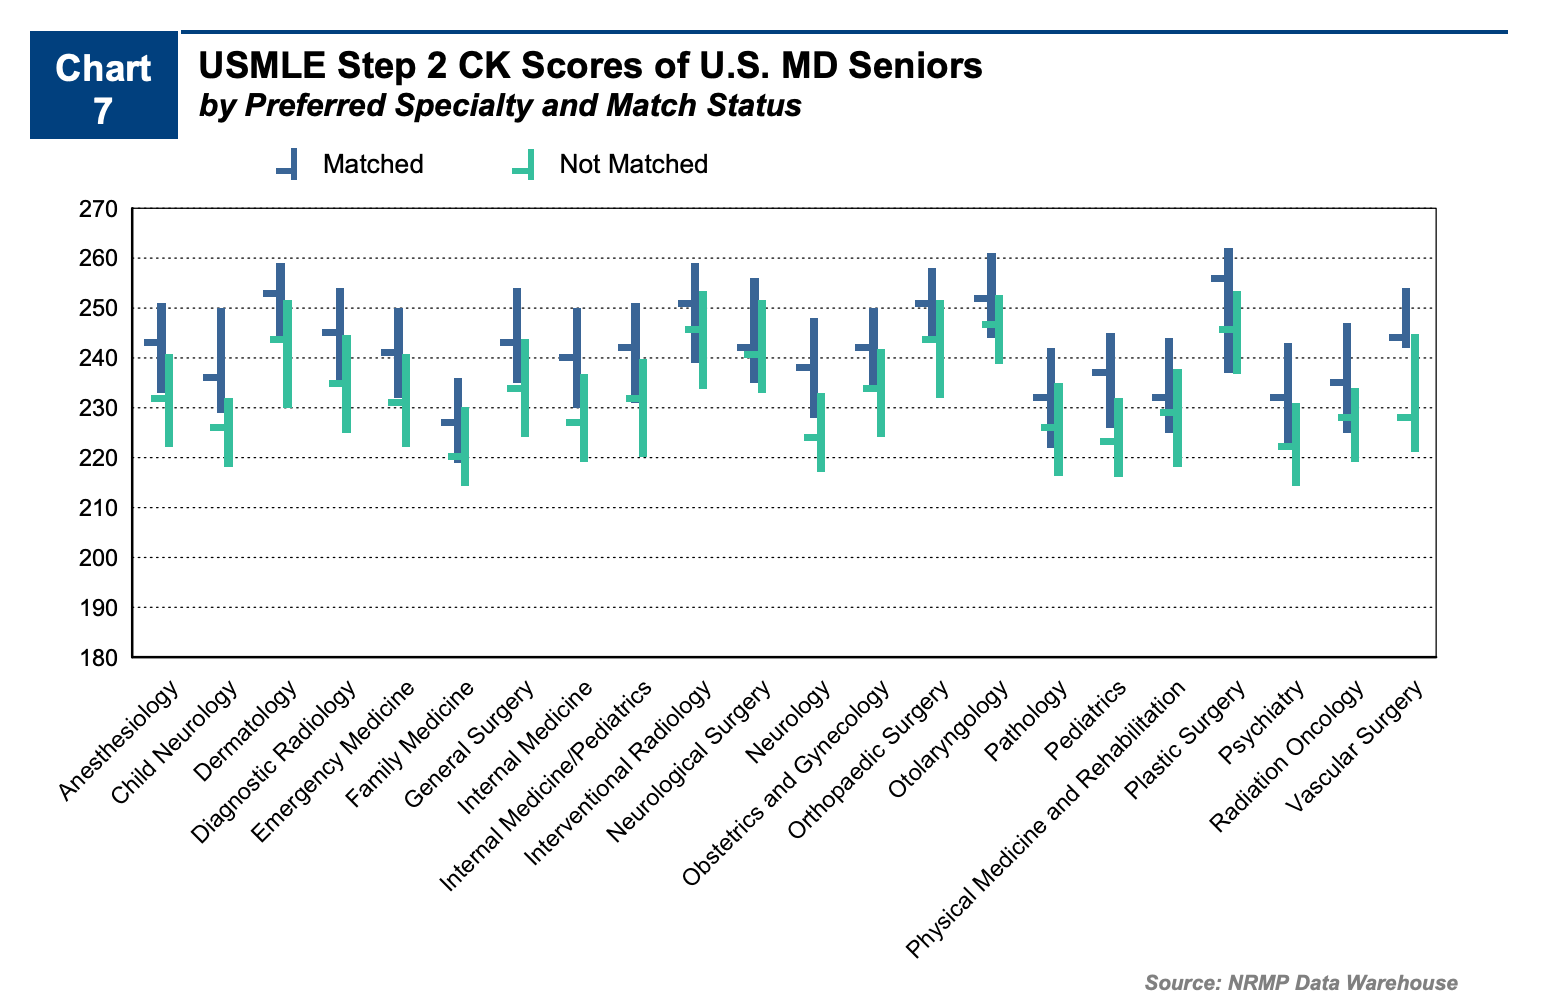
Since AAMC foolishly decided to make Step 1 pass/fail, Step 2 is now the single most important metric for residency selection.
Clinical evals are subjective, and so it makes sense that MCAT is less associated with those.Not consistently associated with success in clinical-based evaluations during the last two “clerkship” years of medical school, including the USMLE step 2 clinical skills evaluation
Step 2 CS is no more - another casualty of COVID19.
Again, clinical evals are subjective. What about objective measures, like the ABSITE exam for surgery residents?Not associated with success on clinical evaluations during the first year of residency after graduating from medical school[/U]
And again, MCAT success is associated with success on the USMLE Step 2 CK, which is very important for getting into the residency you want.

Why not?Nobody disagrees that there was discrimination in the past. But that does not justify discrimination today.
It's the side of a curve. Very, very distorted.Because we are discussing standardized tests, there are hard minimum and maximum boundaries. In your hypothetical, a minimum score of 0 corresponds to two standard deviations below the mean. Since it's impossible to score below 0, the data cannot follow a perfect bell curve—it has to be skewed.
There will be some skew because long tails are cut off, but I do not think deviation from normal distribution are at all significant for our purposes.