• Welcome to the Internet Infidels Discussion Board.

MCATs, Affirmative Action, and DEI, Oh My

This is moronic. You know perfectly well that it's not at all a reference to any indigenous group of people. It's damned near retarded to pretend it is.
Defending yourself against an accusation of using racist slurs... by using two psychonormative slurs in a row instead. Congratulations, you're a walking parody.

I'm neither autistic nor was I ever behind my school level by the way, but I have plenty of good friends who are, and whose moral judgement I'd trust over yours in a heartbeat.
 
We observe small differences between the White and Middle Eastern/North African MCAT and GPAs, but an unexpectedly large difference in acceptance rate. Do we comment "Islamophobia is for realz!", "Whites clearly are rigging the system," or do we try to delve into how this is happening? Likewise, for a comparison between Whites and Asians: Whites have a higher acceptance rate but slightly less GPA and less MCAT. Do we say this is due to racial preferences of propping up White people?

I have written before that acceptance rates are a red herring because they are a function of both selection criteria and the applicant pool. If MCAT/GPA of accepted students are comparable, that means that the selection criteria are likely as well. So most likely the difference is that more MENA students apply. Besides, MENA students have somewhat lower MCATs than whites in your table.

Do we try to blame this on the unseen statistics of the other racial groups and alleged preferences there? Well, in that case, each of the remaining top 3 groups would still be effected equally proportionally and not have such differences, first. Secondly, we're starting to see the idea here: there could be something unseen in the chart that affects the numbers and means by themselves (or means and stdevs) do not necessarily imply racism...
There is a big difference between groups having slight differences (like within top three rows and bottom three rows both) vs. groups having massive differences (like between top three rows vs. bottom three rows). But you want to ignore the big differences with the bottom three rows (you even put a big X through them) and instead pretend that these massive differences are the same as slight differences within the top three rows.
Okay, so how about this? Whatever the variables are that play into the differences we observe when we look at the whole table, those same variables also play some roles in the top three acceptance rate differences, too? Why not be consistent?
Because the differences are bigger.
Here's a possible contributing factor and it might not be the most significant (I don't think it is): foreigners. Foreign citizens cannot apply to most medical schools and the few to which they can apply are difficult to get into. If we suppose that there are relatively quite a few Asian and Middle Eastern foreigners who took the MCAT and are trying to get into medical school, they may be getting rejected at a higher rate and skewing the numbers.
Why do you assume there are no black foreigners - e.g. from African countries?
And anyway, it's a moot point. AAMC has a separate "Non-U.S. Citizen and Non-Permanent Resident" category.
To add--there are more medical schools that accept Canadians for some reason than foreigners in general, but Canadians are going to tend to be White.
And yes, that category also applies to Canadians.
True stories: when I took a break from college I worked at a restaurant and one of my co-workers was an Egyptian doctor working as a dishwasher trying to study for MCATs. He had to achieve a certain threshold to apply where he wanted to go to medical school (I think, if I recall correctly). Also, later on in my actual career, I had a colleague from China who had a MD Phd but he was not trying to take MCATs. In both cases, my recollection is that they did not have to do the same number of years of study to get their medical degrees in their home countries.
Yes, medical education is very different abroad. But most foreign medical graduates just apply for US residencies. Some states are even doing away with that requirement, and are allowing foreign doctors to skip even US residency. So I do not see why a medical doctor from abroad would have to take the MCAT in the first place. Maybe you misremembered and it was the USMLE Steps?
I think the other variables are still on the table from previous discussion. Not an exhaustive list: yes, actual discrimination or adjusting criteria directly in admissions based on race;
Since med schools are not coy about admitting that they did that at least before 2023, I do not think we should dismiss this.
"willingness" to work in underserved areas OR mission fitness differences across demographics,
Declared "willingness" is not binding. And mission fitness is subjective af, and thus a good way to smuggle in racial considerations.
What do you or anyone else think are the root cause(s) for the differences in acceptance rates for the top three rows and what is the evidence for that thinking?
Mostly differences among applicant pools.
 
That's ridiculous. The whole point of a standardized exam is to do exactly that, set some arbitrarily defined corpus of knowledge as "standard" and rate all takers relative to their familiarity with it. It's always "manipulated". There is no other way for it to be. Exams don't pop magically into existence, they are assembled by a committee based on their intersubjective experience and values.
Exams being created by some group does not mean that they are "manipulated". And certainly not in the sense I used it.
So MCAT is created. Every premed knows what's on it, everybody takes the same test, and there are plenty of study materials, some free, others not.

And when a student applies with a 512, that's the score. Adcoms cannot manipulate the 512 to better fit what they want it to be. It is what it is. When a student sends in essays, the adcoms can manipulate their evaluation of it. Because essay evaluations are subjective, they are susceptible to manipulation by adcoms. MCAT scores are not. Even if MCAT didn't fall fully formed from Mount Olympus or something.
 
There used to exist examples of SAT exam questions that were biased towards black students with references to black culture peppered throughout. Not ever actually used but to demonstrate how ‘standardized tests’ were inherently biased towards the culture of this writing the test questions. Predictably white people lost their damn minds because there were questions that flummoxed them.
[citation needed]
And if that happened, it should not have.
 
We observe small differences between the White and Middle Eastern/North African MCAT and GPAs, but an unexpectedly large difference in acceptance rate. Do we comment "Islamophobia is for realz!", "Whites clearly are rigging the system," or do we try to delve into how this is happening? Likewise, for a comparison between Whites and Asians: Whites have a higher acceptance rate but slightly less GPA and less MCAT. Do we say this is due to racial preferences of propping up White people?

I have written before that acceptance rates are a red herring because they are a function of both selection criteria and the applicant pool. If MCAT/GPA of accepted students are comparable, that means that the selection criteria are likely as well. So most likely the difference is that more MENA students apply. Besides, MENA students have somewhat lower MCATs than whites in your table.

Do we try to blame this on the unseen statistics of the other racial groups and alleged preferences there? Well, in that case, each of the remaining top 3 groups would still be effected equally proportionally and not have such differences, first. Secondly, we're starting to see the idea here: there could be something unseen in the chart that affects the numbers and means by themselves (or means and stdevs) do not necessarily imply racism...
There is a big difference between groups having slight differences (like within top three rows and bottom three rows both) vs. groups having massive differences (like between top three rows vs. bottom three rows). But you want to ignore the big differences with the bottom three rows (you even put a big X through them) and instead pretend that these massive differences are the same as slight differences within the top three rows.
Okay, so how about this? Whatever the variables are that play into the differences we observe when we look at the whole table, those same variables also play some roles in the top three acceptance rate differences, too? Why not be consistent?
Because the differences are bigger.
Here's a possible contributing factor and it might not be the most significant (I don't think it is): foreigners. Foreign citizens cannot apply to most medical schools and the few to which they can apply are difficult to get into. If we suppose that there are relatively quite a few Asian and Middle Eastern foreigners who took the MCAT and are trying to get into medical school, they may be getting rejected at a higher rate and skewing the numbers.
Why do you assume there are no black foreigners - e.g. from African countries?
And anyway, it's a moot point. AAMC has a separate "Non-U.S. Citizen and Non-Permanent Resident" category.
To add--there are more medical schools that accept Canadians for some reason than foreigners in general, but Canadians are going to tend to be White.
And yes, that category also applies to Canadians.
True stories: when I took a break from college I worked at a restaurant and one of my co-workers was an Egyptian doctor working as a dishwasher trying to study for MCATs. He had to achieve a certain threshold to apply where he wanted to go to medical school (I think, if I recall correctly). Also, later on in my actual career, I had a colleague from China who had a MD Phd but he was not trying to take MCATs. In both cases, my recollection is that they did not have to do the same number of years of study to get their medical degrees in their home countries.
Yes, medical education is very different abroad. But most foreign medical graduates just apply for US residencies. Some states are even doing away with that requirement, and are allowing foreign doctors to skip even US residency. So I do not see why a medical doctor from abroad would have to take the MCAT in the first place. Maybe you misremembered and it was the USMLE Steps?
I think the other variables are still on the table from previous discussion. Not an exhaustive list: yes, actual discrimination or adjusting criteria directly in admissions based on race;
Since med schools are not coy about admitting that they did that at least before 2023, I do not think we should dismiss this.
"willingness" to work in underserved areas OR mission fitness differences across demographics,
Declared "willingness" is not binding. And mission fitness is subjective af, and thus a good way to smuggle in racial considerations.
What do you or anyone else think are the root cause(s) for the differences in acceptance rates for the top three rows and what is the evidence for that thinking?
Mostly differences among applicant pools.
Can you explain why it is preferable to admit students who are unlikely —by their own stated goals—vs admitting also well qualified students who state they are interested in working in underserved areas?
 
Why do you think knowledge and reasoning are the only, or the most, or even significantly important indicators of which already qualified candidates are likely to become the best doctors?
I never said "only", but I definitely think they they are significantly important. Probably the most important, and even if not, they are certainly the most important metrics that can be usefully measured in undergrads.
Why do I think that? Because human bodies are complex, as are disease processes. And reasoning ability is about taking all this complex knowledge and coming up with a solution.
Why do you think otherwise? What do you think are "significantly important indicators" that med schools should focus on instead? Melanin content? What language someone's ancestors spoke? Presence of epicanthic folds?
Sure; But you can evaluate them based on their interpersonal skills and their interactions with other humans - one time honoured way to do this is by interviewing them.
And I never said that interpersonal skills are not important, or you should not interview people. But I'd much rather have a knowledgeable and intelligent Dr. House than somebody with a great bedside manner who is neither of those two.
Interviews are also inherently subjective, and thus susceptible to interviewer bias, whether conscious or not. Interview (or essay) scores can be used to systematically downgrade groups you want fewer of, like Harvard College giving Asian students unfavorable personality scores in order to justify admitting fewer of them.
Success at interview isn't only about answering the interviewer's questions in such a way as to be technically correct.
Interviews are not a great way to assess candidates - but then, nor are standardised test scores.
If Bilby were in charge of medical school admissions, how would you do it? For that matter, do you know how things are run in Australia?
 
Such cool reasoning powers demonstrated by your devolution into insults and name calling…
You've spent pages calling people racists, and insinuating that all disagreement to your beliefs is evidence of bigotry... and you're deeply offended by Bomb accurately describing your interactions as tribalistic?
I believe the point was that the pot was calling the kettle black. That you missed the point is not ironic, even given your post 788.
I think the point is that some people, including Toni, can dish it out but can't take it. And by that I mean they'll fling out insults with abandon, but the merest whiff of criticism of their behavior is the insult to end all insults.
Whoosh - it went past you once again. Perhaps if you weren't so intent on whiteknighting a fellow tribal member, you'd get it.
I'm not whiteknighting anyone. Nobody needs saving, least of all from me.

But I do dislike bullies, and I'll call them on their bullshit attempts to force compliance to their beliefs whenever I run across it.
BTW, if you don't think there are at least 2 racial bigots participating in this thread, then you are not very smart.
It's possible that there are some actual racists in here. But I don't think that's the case.

But I do understand that it's a really, really, really easy claim to make. And it's as unfalsifiable as calling someone a witch, and if they say they're not well that's just what witches would say.
 
If noting that people engage in tribal thinking - which you 100% know means in-group assumed morally right, out-group cast as bad - is "racist", then you, sir, are not very smart.
Yes. That is exactly what I mean. Using loaded and historically racialized terms as a stand in the general concept of anri-social behavior is racist. Your Colonislism-shaped beliefs about what "tribes" are like is wrong, prejudicial, and speaks volumes about how you see the world. It is also, given the cause you are supposedly championing, incredibly ironic.
Oh for the love of reason stop trying to channel Judith Butler's style of empty rhetoric.

Seriously, all you have are school-yard taunts. You just wrap them up in a transparent veneer of academia as if that makes them meaningful. You're a fucking bully, Poli.
 
This is moronic. You know perfectly well that it's not at all a reference to any indigenous group of people. It's damned near retarded to pretend it is.
Defending yourself against an accusation of using racist slurs... by using two psychonormative slurs in a row instead. Congratulations, you're a walking parody.

I'm neither autistic nor was I ever behind my school level by the way, but I have plenty of good friends who are, and whose moral judgement I'd trust over yours in a heartbeat.
I'm calling it as I see it. Your arguments are dumb, they're framed in idiotic ways. You rely on big words and condescension to make yourself feel like you're in the moral right... all while you treat others with absolute contempt and intolerance.
 
  • I Agree
Reactions: WAB
That's ridiculous. The whole point of a standardized exam is to do exactly that, set some arbitrarily defined corpus of knowledge as "standard" and rate all takers relative to their familiarity with it. It's always "manipulated". There is no other way for it to be. Exams don't pop magically into existence, they are assembled by a committee based on their intersubjective experience and values.
Exams being created by some group does not mean that they are "manipulated". And certainly not in the sense I used it.
So MCAT is created. Every premed knows what's on it, everybody takes the same test, and there are plenty of study materials, some free, others not.

And when a student applies with a 512, that's the score. Adcoms cannot manipulate the 512 to better fit what they want it to be. It is what it is. When a student sends in essays, the adcoms can manipulate their evaluation of it. Because essay evaluations are subjective, they are susceptible to manipulation by adcoms. MCAT scores are not. Even if MCAT didn't fall fully formed from Mount Olympus or something.
So stop treating it like is fallen from Mount Olympus. Much of what you say is accurate. It's a standardized exam. It has all the strengths and weaknesses ofvl a standardized exam. To use it as one factor in an admissions decision is reasonable. To use it as the sole factor would be insane. Automatic cut offs around GPA or test scores used to be popular, but the university system largely turned its back on those kinds of simplistic culling methods, for a host of reasons. While demonstration of in-built race and class biases was one of those reasons, it was not the only reason, and pretending that is was is dishonest, whether you are a rando on the internet or our barely-educated President of the United States.
 
Last edited:
Wow. You admit that the data on failing to complete in medical school is not a clean indicator of academic performance, yet persist in looking at MCAT and GPA scores. Your hobby horse must have pretty good padding on it since you've been riding it so hard.
Will you give it a rest with the "hobby horse" nonsense? Step 1 failure is pretty clean as far as failing for academic reasons, and it shows a strong association with MCAT and GPA. Also, while not graduating may not be "clean" as you call it since people may drop out for non-academic reasons, the association with MCAT and GPA indicates that academic reasons are a major reason for dropping out of med school. There is no reason why non-academic reasons should be associated with MCAT/GPA, but there are reasons why academic failure in med school should be associated with academic performance in undergrad (MCAT/GPA).

In fact, those who believe that academic performance in med school is for some reason unrelated to academic performance in undergrad should show evidence for it.
I made no assumption. I pointed out that your analysis ignores many possible causal factors because of your obsession with race. Unlike you, I don't pretend to know the underlying causes, but as many others have pointed out, the requisite date is either insufficiently granular or nonexistent.
I do not believe you that you make no assumptions. You would not be arguing this hard on the side of Toni, Don2 etc. if you didn't.
 
Wow. You admit that the data on failing to complete in medical school is not a clean indicator of academic performance, yet persist in looking at MCAT and GPA scores. Your hobby horse must have pretty good padding on it since you've been riding it so hard.
Will you give it a rest with the "hobby horse" nonsense?
Lead the way.
Derec said:
Step 1 failure is pretty clean as far as failing for academic reasons, and it shows a strong association with MCAT and GPA. Also, while not graduating may not be "clean" as you call it since people may drop out for non-academic reasons, the association with MCAT and GPA indicates that academic reasons are a major reason for dropping out of med school.
Sorry, but “association “ does not indicate whether a variable is a major reason for anything, especially in an under specified model.

Derec said:
I made no assumption. I pointed out that your analysis ignores many possible causal factors because of your obsession with race. Unlike you, I don't pretend to know the underlying causes, but as many others have pointed out, the requisite date is either insufficiently granular or nonexistent.
I do not believe you that you make no assumptions. You would not be arguing this hard on the side of Toni, Don2 etc. if you didn't.
I didn’t say I made no assumptions. I said I made no assumption about a particular issue.

Your analysis rests on multiple assumptions and a refusal to consider many possible mitigating factors. It is unconvincing.
 
"Affirmative action" is a big problem in India, since it bars at least (many times more) 50% of seats in education, government service and political positions to people belonging to what is known as "Other Backward Classes: (27%). Scheduled Castes (16.5%) and Scheduled Tribes (7.5%). The classification is dependent on the government of the state on the day. In the process, many young people of castes not belonging to these categories are denied oplportunities, though they may be better qualified. The Constitution formed this rule for 10 years, but it continues even after 78 years due to democratic politics.
 
Such cool reasoning powers demonstrated by your devolution into insults and name calling…
You've spent pages calling people racists, and insinuating that all disagreement to your beliefs is evidence of bigotry... and you're deeply offended by Bomb accurately describing your interactions as tribalistic?
I believe the point was that the pot was calling the kettle black. That you missed the point is not ironic, even given your post 788.
You're using a racist metaphor -- it's implying there's something wrong with being black. For shame! [/Politesse]
 
I was referring to individuals' habits of thought, not to social organization.
Yeah. I know. With a racist metaphor.

Yes, I know you didn't mean that. You just said that. It's not fair to hold you accoutnable for what you say, only what you mean, and we can never really know what you mean, except through what you say. Magic.

:thinking:
:picardfacepalm:
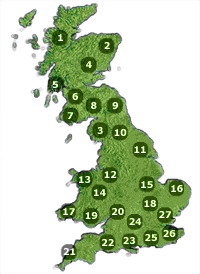
Can you remind me which race "tribe" is a racist slur against?

d8b7c554fa6797bc733d185e4a20d07025e8ae54.gif

...
26: Cantiaci
...
Are you pretending to be dumb for some rhetorical reason, or just to waste our time?
Are you pretending to be semiliterate for some rhetorical reason, or are you in fact not pretending? Either way, why are you insulting me using a slur against mute people?

Even if you did mean, by smearing your interlocutors as "tribal", only to compare them to the Cantiacci (as we all know you most certainly did not) your comment would still be ethnocentric, bigoted, and factually misleading, just on the basis of political type rather than skin color.
Do you use that sort of rhetorical tactic to suppress ideological nonconformism among your students? As we all know, I most certainly did not mean to compare them to any particular tribe. And your vicious and baseless insinuation that I was specifically comparing them to some other tribes of your choice has no more merit than your vicious and baseless insinuation that I'm trying to pass myself off as comparing them to the Cantiaci. As I said, and as you quoted back to me and said you knew, I was referring to individuals' habits of thought, not to social organization. I posted a list of Britain's tribes not to say I meant to compare anyone to those tribes but rather to refute your stupid religion's dogma that using "tribal" in the psychological sense is a racist metaphor. White people are as naturally prone to being tribal as anyone else -- tribal societies are common to all races; they form in response to environmental factors, not because of population-specific gene variants; and those who coined the use of "tribal" as a metaphor to describe psychology were familiar with white people having tribes.

If you aak an archaeologist rather than a right-wing blowhard, they'll happily correct you on your misguided beliefs that the period before Roman imperialization was more violent or even more culturally insular than what followed.
Stop strawmanning infidels. You know perfectly well I was not alleging any violent tendencies but rather pointing out Toni's peculiar focus on whole ethnic groups instead of individuals, and her irrational presumption that Derec shared that peculiar focus. My supposed "misguided beliefs that the period before Roman imperialization was more violent or even more culturally insular" are misguided beliefs you just made up out of whole cloth and imputed to me because you don't give a rat's ass whether the things you say about opponents are true. And as far as the Roman conquest goes, if you ask a classicist rather than a left-wing blowhard she'll happily inform you that Rome had tribes too.
 
Perhaps Asians apply less frequently to schools with no or lower requirements. In fact, HBCUs on average have lower thresholds and very little Asian enrollment. I think it's like 1%. HBCUs are only a subset of such schools.
That does not explain why the difference in average MCAT scores also exists for individual schools like Duke. Schools don't generally publish such race-level data, but we have them for Duke because of a recent investigation.
Carolina Journal said:
For the 2024-25 admissions cycle, HHS said 3.3% of white applicants and 3.4% of Asian applicants were admitted to the medical school, compared with 10% of black applicants and 6.7% of Hispanic applicants.
The agency also pointed to differences in average Medical College Admission Test (MCAT) scores among admitted students. Black students admitted during that cycle had an average MCAT score in the 87th percentile, and Hispanic students averaged in the 89th percentile, compared with the 97th percentile for white students and 98th percentile for Asian students.
The agency also said it asked Duke to explain differences in MCAT scores and grade-point averages among racial groups, but did not receive a responsive explanation.
From here.

_Some_ Asians are foreigners who can only apply to a few elite schools. This is not true for the AN/NA cohort.
"Non-U.S. Citizen and Non-Permanent Resident" is actually a separate AAMC category, which means that Russians, Chinese, Nigerians and Colombians on student visas are not included in the white, Asian, black and Hispanic categories, respectively.
Perhaps Asians more often would not want to go to a safety school, but would rather go into pharma, biotech, biomedical engineering etc. We use acceptance rates and matriculant rates as the same, but Stanley Zhong shows one can get accepted but not go.
Pure speculation that this differs by race to any significant extent.
Perhaps less Asians show willingness to participate in missions to work in underserved communities. Examples: tribal areas/reservations.
There are underserved communities everywhere. Rural Appalachia, swamps of Louisiana (straight from True Detective!), Atlanta hood.
And it is again pure speculation that fewer (not less, Asians are countable!) Asians engage in such activities.
None of this is intended to state there are no issues of discrimination against Asians. Just that it is an assumption that all or most of the observed differences are due to discrimination.
Med schools are not even denying that they engaged in racial preferences prior to the SCOTUS decision. Did they change their practices, or are simply hiding it behind things like "mission fit"? I think that if they really had stopped discriminating by race, then the characteristics of their admitted classes, and the characteristic of AAMC data overall, should change significantly.
ETA: So perhaps it is also true that Harvard, Yale, and a few other medical schools use race to adjust admission criteria/scores and a majority of medical schools do not do that.
A lot of "perhaps".

First, the Duke example is interesting, but it doesn't prove your broader point for a few reasons. (1) Perhaps Duke did engage in discrimination--single data points and outliers certainly exist. (2) However, to genuinely demonstrate discrimination, you have to look at the holistic adcom scoring. It is typical for investigating agencies to only publicize the specific data points (like MCAT scores) that support their probable cause for criminal charges or preponderance of evidence for civil, while publicly withholding the rest of the application data that the defending entity might use. (3) The Duke data actually highlights why we cannot simply extrapolate from MCAT means. As Jimmy Higgins pointed out, nationally we observe a rough correlation where acceptance rates increase alongside increasing MCAT scores across racial cohorts. Duke is an anomaly: the acceptance rates for Asians and Whites are actually lower than that of Blacks. This outlier underscores exactly why multi-variate analysis is necessary, and why merely pointing at a difference in MCAT means is statistically inadequate.

Next, regarding foreign applicants and how the AAMC tracks them, you've made a factual error. Take a close look at the AAMC data, specifically the MCAT tables. Directly above the list of races, the columns are merged under the header: "All Applicants (Regardless of Citizenship and Permanent Residency Status)."

1790082829957.png

I understand the mistake, as I initially made it too due to popular narratives that slice up racial data without looking at the fine print. You can easily confirm that foreigners are embedded in the race counts with basic arithmetic: sum the counts left-to-right from NA/AN to Race/Ethnicity Unknown, and you get the Total Applicants. Then, sum the US Citizens + Permanent Residents + Non-US Citizens/Non-Permanent Residents, and you get the exact same Total Applicants number. The point is not moot. It is real data, and there is only one logical conclusion.

Additionally, the mean MCAT for these non-citizen/non-resident applicants is 507.5, which is higher than the overall US citizen/permanent resident average and much closer to the White (508.0) and Asian means than other racial cohorts (example: Black 498.1). It is highly plausible that there is disproportionate representation of Asians, MENA, and Whites within this cohort. Because foreign applicants face massive institutional barriers, they are a deprioritized group for most medical schools, which is why their acceptance rate is abysmal (roughly 228/2020 or ~11.3%). Embedding a group with high MCAT scores but extremely low acceptance rates into the racial aggregates introduces significant noise at a minimum, and heavy statistical skews at a maximum.

As for your claim about underserved communities, simply asserting they are "everywhere" is hyperbole used to handwave away a plausible variable. I never claimed there are zero people of a certain demographic working in these communities either; I pointed out they participate at different rates. A study was already submitted to this thread demonstrating exactly this: Native American medical doctors showed the highest rates of participation in these communities, while Asian medical doctors showed the lowest. The inference that where one student demographic eventually will (want to) work as a medical doctor will show up in aggregate trends is reasonable. So, this plausible variable as it applies to aggregates absolutely still stands.

Looking at your remaining points, let's review how this discussion has actually unfolded. Your core assumption relies on posting a graph of MCAT means differences and effectively saying, "Aha! That proves a prevalent culture of discrimination." Jimmy Higgins countered by showing that, nationally, acceptance rates generally scale with MCAT means. I have repeatedly demonstrated that significant confounding variables drive this variation.

You have been unreasonably dismissive of these variables, even when hard data (like the AAMC table math, the underserved community study or data described in other posts) shows otherwise. Specific instances of discrimination might be one cause of variation among many. However, you cannot submit a single-variable graph and conclude it is the vast majority reason for those differences, especially when ignoring the multivariate reality of admissions.
 
Last edited:
Not only are/were universities using DEI in their admissions process, they used it on students already admitted!: :LOL:

Stanford R&DE Uses AI to Race Swap Students for Advertising

Stanford University is facing backlash after its Residential & Dining Enterprises used a photograph of students that had been edited by artificial intelligence—including entirely changing one Hispanic, male student into a Black woman—in its advertising.

The photo first came to light in a report by The Stanford Review, the university’s right-leaning student newspaper. The original image shows a female student on the left and two male students to her left, with all three smiling at the camera and posing with their food outside Star Ginger, a food stall in one of Stanford’s dining halls; the AI-edited image removed the rightmost male student and generated a Black woman in his place.

The one thing that's a little baffling is they chose to erase the Hispanic guy, rather than the White guy in the middle. Did Hispanic males drop below even White males on the progressive stack? Or maybe they thought the Hispanic guy was also White?!

Altering the Asian girl's face had to sting a little for her. I guess AI (or the photo editor) wasn't too fond of her chubby cheeks. I kinda liked her better the original way.
 
Last edited:
We should naturally expect an astronomically high R2 here. When you use four parameters (an intercept plus three variables) to model just five aggregate data points, the math will inevitably draw a line that perfectly intersects almost every point. (You can also see the statistical noise of overfitting in the coefficients themselves--the GPA multiplier actually turns negative purely because it is so heavily correlated with the MCAT). With so little aggregate data and so many variables, the model overfits by design.

Therefore, it is important to note this is a test to explore plausibility and confirm that this is a plausible explanation, not to provide a definitive proof. We cannot really see what happens behind the scenes. In reality, perhaps some people are implementing something nefarious. Perhaps others are being lazy and using race as a proxy for these public goods. While others may be doing the rigorous math of using criteria in admissions that includes mission fitness, and we are simply observing the results in the aggregate.

To add--we still do not know how much of the differences are due to matriculating to different schools with different thresholds. We observed how much Puerto Rico can affect the numbers. There isn't much data on the matriculation side of this.
The negative effect on GPA is surprising, but in general I agree with what you're saying. However, I have issues:

1) I find the lack of consideration of the flunk-out rate important.

2) As you say, race might be being used as an easy proxy. The problem is that once proxies are recognized they cease to become good predictors. They will be gamed. We actually end up selecting for the children of well to do parents.
 
"To add--we still do not know how much of the differences are due to matriculating to different schools with different thresholds. We observed how much Puerto Rico can affect the numbers. There isn't much data on the matriculation side of this."

Much of the data is unavailable to do this kind of analysis, especially school-specific. There are some interesting observations to be made, however, at a regional and state level. Some states (like West Virginia) and territories (like Puerto Rico) have acceptance rates higher than there are for the White and Asian cohorts. Compared to a state like California with elite MCAT scores and GPAs, those acceptance rates often shoot past California while those regions' MCATs and GPAs are not as good. These regions generally have small Asian populations, but sometimes large White populations or other demographics. The acceptance rate of California in general, while "high," is less than that of either White or Asian, even though the average scores are comparable. This is suggestive of regional bottlenecking discussed earlier, but I cannot really be certain because of the lack of data on exactly where people matriculate to and those demographic and score statistics for those schools. I kind of think that "mission fitness" or seeking diversity as a "public good" is interactive with regional bottlenecking, magnifying the effect. Still, I do not know how much specific schools with specific charters or merely voluntarily not going to schools with lower thresholds plays a role as well.

I will finish computing and show some numbers later.
I think the issue here is that you don't want to keep bedding the numbers. The numbers are telling us something that isn't unexpected, and appears reasonable. That better grades mean better acceptance rates. This entire thread has people who are woke beyond belief desperately trying to find data that implies the nation is unfair to whites and Asians. The data broadly says, better students do better. Trying to get SDs to a certain level is merely an exercise in skill at getting the results you want at some point.
Look again at what he's doing. He's finding the bias we are talking about, but making up a mission fitness parameter to balance it--but we have no evidence that it's relevant.
 
Back
Top Bottom